Back to all case studies
Patient case Study
Laura’s transition to CREXONT extended-release capsules
Explore how less frequent dosing shaped her treatment decision
Laura’s Diagnostic Journey
Laura was diagnosed in 2014 when she was 52. She had been experiencing symptoms prior to her diagnosis, including freezing of gait, rigidity, mood changes, and involuntary leg movements. It took multiple doctor visits before being referred to a Movement Disorder Specialist, who confirmed Laura’s diagnosis of Parkinson’s disease.
Laura’s Previous Treatment
- Dopamine agonist
- IR CD/LD
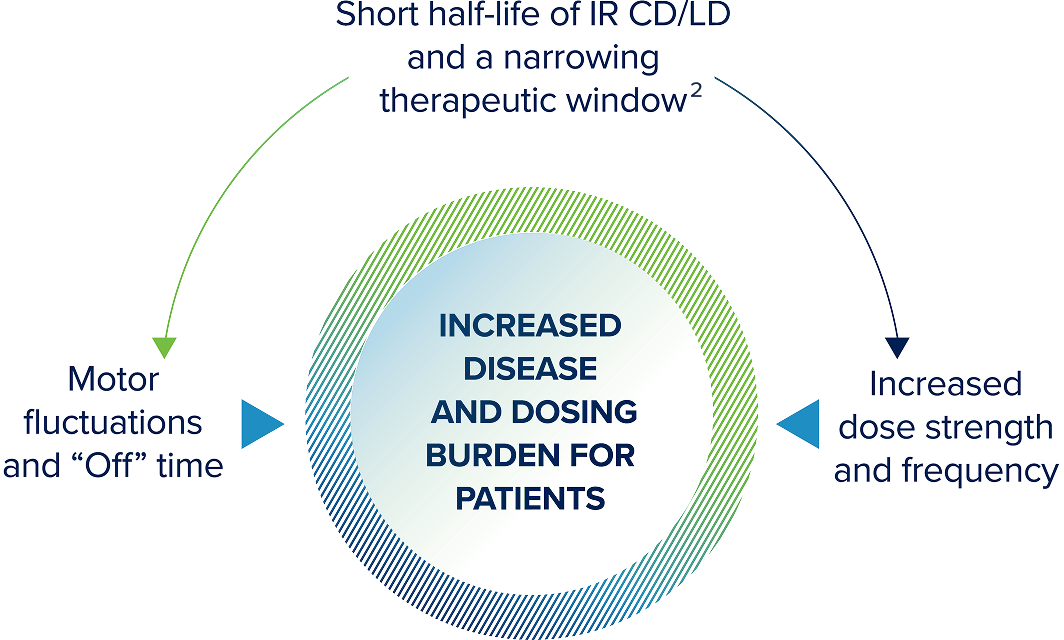
“It felt like I was living by a stopwatch.
It created a kind of mental noise that never stopped.”
—Laura
Laura’s Switch to CREXONT
- Two 70/280 mg (carbidopa/levodopa) capsules three times daily

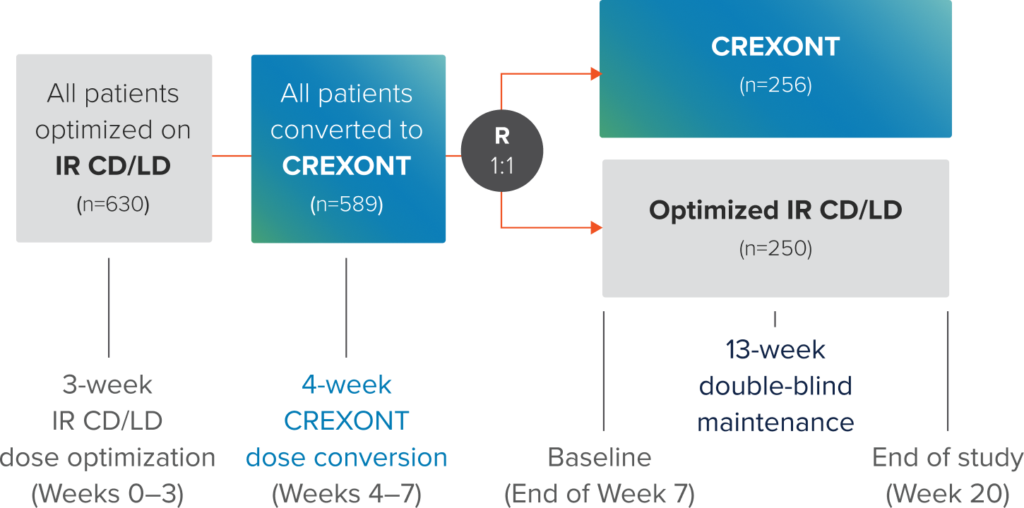
The Phase 3 RISE-PD study
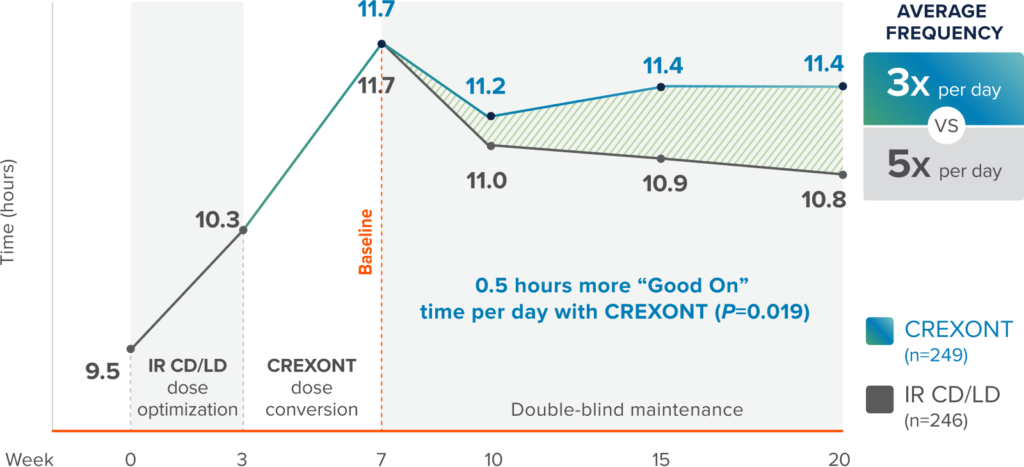
CREXONT demonstrated a statistically significant improvement in “Good On” time (0.5 hours per day) with patients taking CREXONT vs optimized IR CD/LD in the RISE-PD head-to-head study (P=0.019) with an average dosing frequency of 3 vs 5 times a day.1
“Good On” time per day1,3,4
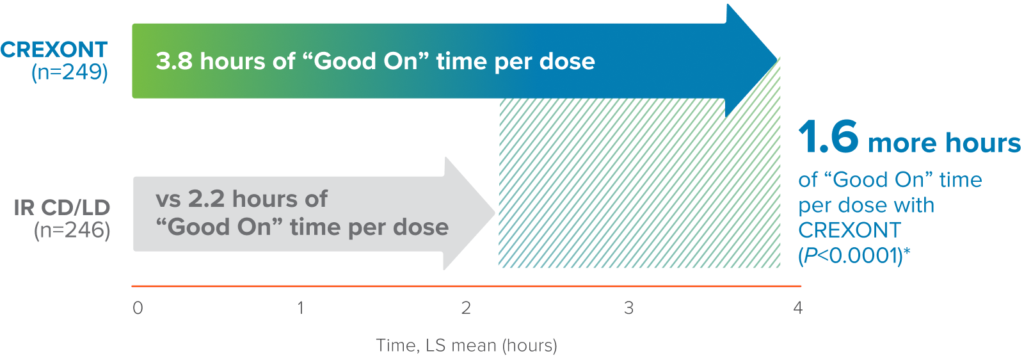
*1.6 more hours per dose is the LS mean difference.
Laura’s Life With CREXONT1
Since starting CREXONT, Laura has not experienced side effects. In collaboration with her healthcare provider, she adjusted her CREXONT dose to two 70/280 mg (carbidopa/levodopa) capsules four times daily after experiencing some “Off” time between doses. Now, she’s enjoying the activities important to her, including her role as an active Parkinson’s disease advocate.
Laura’s experience with CREXONT is her own and may not reflect the experience of every patient. For some patients, CREXONT may cause falling asleep during daily activities. Side effects may include nausea and anxiety. Individual results will vary. Talk to your patients to see if CREXONT is right for them.

Adverse reactions occurring in at least 2% of patients treated with CREXONT® (carbidopa and levodopa) extended-release capsules while converting from IR CD/LD and at a higher rate than IR CD/LD in the double-blind maintenance period1:
| Dose conversion period | Double-blind period | ||
| ADVERSE REACTION | CREXONT(n=589) | CREXONT (n=256) | IR CD/LD (n=250) |
|---|---|---|---|
| Nausea | 5% | 4% | 1% |
| Anxiety | 2% | 3% | 0% |
| Dizziness | 3% | 2% | 1% |
| Dyskinesia | 7% | 2% | 0.4% |
| Constipation | 2% | 2% | 0.4% |
| Headache | 2% | 1% | 0% |
| Vomiting | 2% | 1% | 0% |
| Insomnia | 2% | 1% | 0.4% |
“The scheduling has done wonders to my life.
Not being driven by the schedule has been divine.”
—Laura

Use the dosing tool to convert from IR CD/LD to CREXONT
Learn how CREXONT can fit your patients’ needs, and find out how to convert your appropriate patients from IR CD/LD to CREXONT.
Find out about savings programs for your patients
IMPORTANT SAFETY INFORMATION
Indications and Usage
CREXONT® (carbidopa and levodopa) extended-release capsules for oral use is indicated for the treatment of Parkinson’s disease, post-encephalitic parkinsonism, and parkinsonism that may follow carbon monoxide intoxication or manganese intoxication in adults.
Dosage and Administration
- Evaluate vitamin B6 levels before and during treatment with carbidopa/levodopa therapies.
- Levodopa-naïve patients: Starting dose is 35 mg carbidopa/140 mg levodopa taken orally twice daily for the first three days; thereafter, dosage may be increased gradually as needed
- For patients converting to CREXONT from immediate-release carbidopa/levodopa, dosages are not substitutable on a 1:1 basis. See full prescribing information Section 2.2 for instructions
- For patients converting from Rytary® (carbidopa and levodopa) extended-release capsules, initiate CREXONT on an approximately 1:1 mg basis using the levodopa component for conversion
- CREXONT may be taken up to four times daily. The maximum recommended daily dosage is 525 mg carbidopa/2100 mg levodopa
- CREXONT may be taken with or without food. CREXONT capsules should not be chewed, divided or crushed. For patients who have difficulty swallowing, the capsule can be opened and the entire contents can be sprinkled on a small amount of applesauce and consumed immediately without chewing. Patients should not store the drug/food mixture for future use.
- CREXONT should not be taken with alcohol
Contraindications
Nonselective MAO inhibitors.
Warnings and Precautions
- CREXONT may cause falling asleep during activities of daily living, somnolence or dizziness. Patients should avoid activities that require alertness such as driving and operating machinery until they know how CREXONT affects them
- It is important to avoid sudden discontinuation or rapid dose reduction to reduce the risk of withdrawal symptoms such as high fever or confusion. Patients who are discontinuing CREXONT should taper off with healthcare provider guidance
- Consider dose reductions or stopping CREXONT in patients with hallucinations or impulse control disorders (e.g., gambling, sexual urges, or uncontrolled spending)
- Consider dose reduction in patients with dyskinesia
- Treatment with carbidopa/levodopa, including CREXONT, may contribute to reduced vitamin B6 levels. Seizures associated with vitamin B6 deficiency have been reported. Seizures were refractory to traditional anti-seizure medications and were only resolved after vitamin B6 administration. Supplement with vitamin B6 as necessary
- Other symptoms of vitamin B6 deficiency may occur, including depression, confusion, cheilosis, glossitis, dermatitis, anemia, and/or neuropathy. Supplement with vitamin B6 as necessary
- Patients with a major psychotic disorder should not be treated with CREXONT
- Monitor patients with a history of cardiovascular disease for cardiac function
- Monitor patients with a history of peptic ulcer for upper GI hemorrhage
- Monitor patients with glaucoma for increased intraocular pressure
Adverse Reactions
The most common adverse reactions (incidence ≥ 3% and greater than immediate-release CD/LD) are nausea and anxiety.
Drug Interactions
Iron salts and dopamine D2 antagonists, including metoclopramide, may reduce the effectiveness of CREXONT.
Use in Specific Populations
Pregnancy: Based on animal data, CREXONT may cause fetal harm. There are no adequate data on the developmental risk associated with the use of CREXONT in pregnant women.
Breastfeeding: The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for CREXONT.
Geriatric patients: There were no differences in safety outcomes between patients less than 65 years of age, 65-75 years of age, or 75 years and older.
To report SUSPECTED ADVERSE REACTIONS, contact Amneal Global Patient Safety at 1‑877‑835‑5472, or FDA at 1‑800‑FDA‑1088 or www.fda.gov/medwatch
Please see full Prescribing Information for CREXONT.
Content is for guidance only. Please use clinical judgment when prescribing CREXONT. Dosage is individualized for each patient.
References: 1. CREXONT [package insert]. Bridgewater, NJ: Amneal Pharmaceuticals LLC; 2024. 2. Olanow CW, Obeso JA, Stocchi F. Drug insight: continuous dopaminergic stimulation in the treatment of Parkinson’s disease. Nat Clin Pract Neurol. 2006;2(7):382-392. 3. Hauser RA, Decker F, Lehert P. Parkinson’s disease home diary: further validation and implications for clinical trials. Mov Disord. 2004;19(12):1409-1413. 4. Hauser RA, Espay AJ, Ellenbogen AL, et al. IPX203 vs immediate-release carbidopa-levodopa for the treatment of motor fluctuations in Parkinson disease: the RISE-PD randomized trial. JAMA Neurol. 2023;80(10):1062-1069.